340B hospitals carry 99.0% of $3.10 billion in 2027 outpatient losses
CMS softened the 340B drug cut to ASP minus 28% and the remedy offset to 2.0 points. In our run of the CMS hospital file, 340B hospitals still hold 99.0% of $3.10 billion in losses.
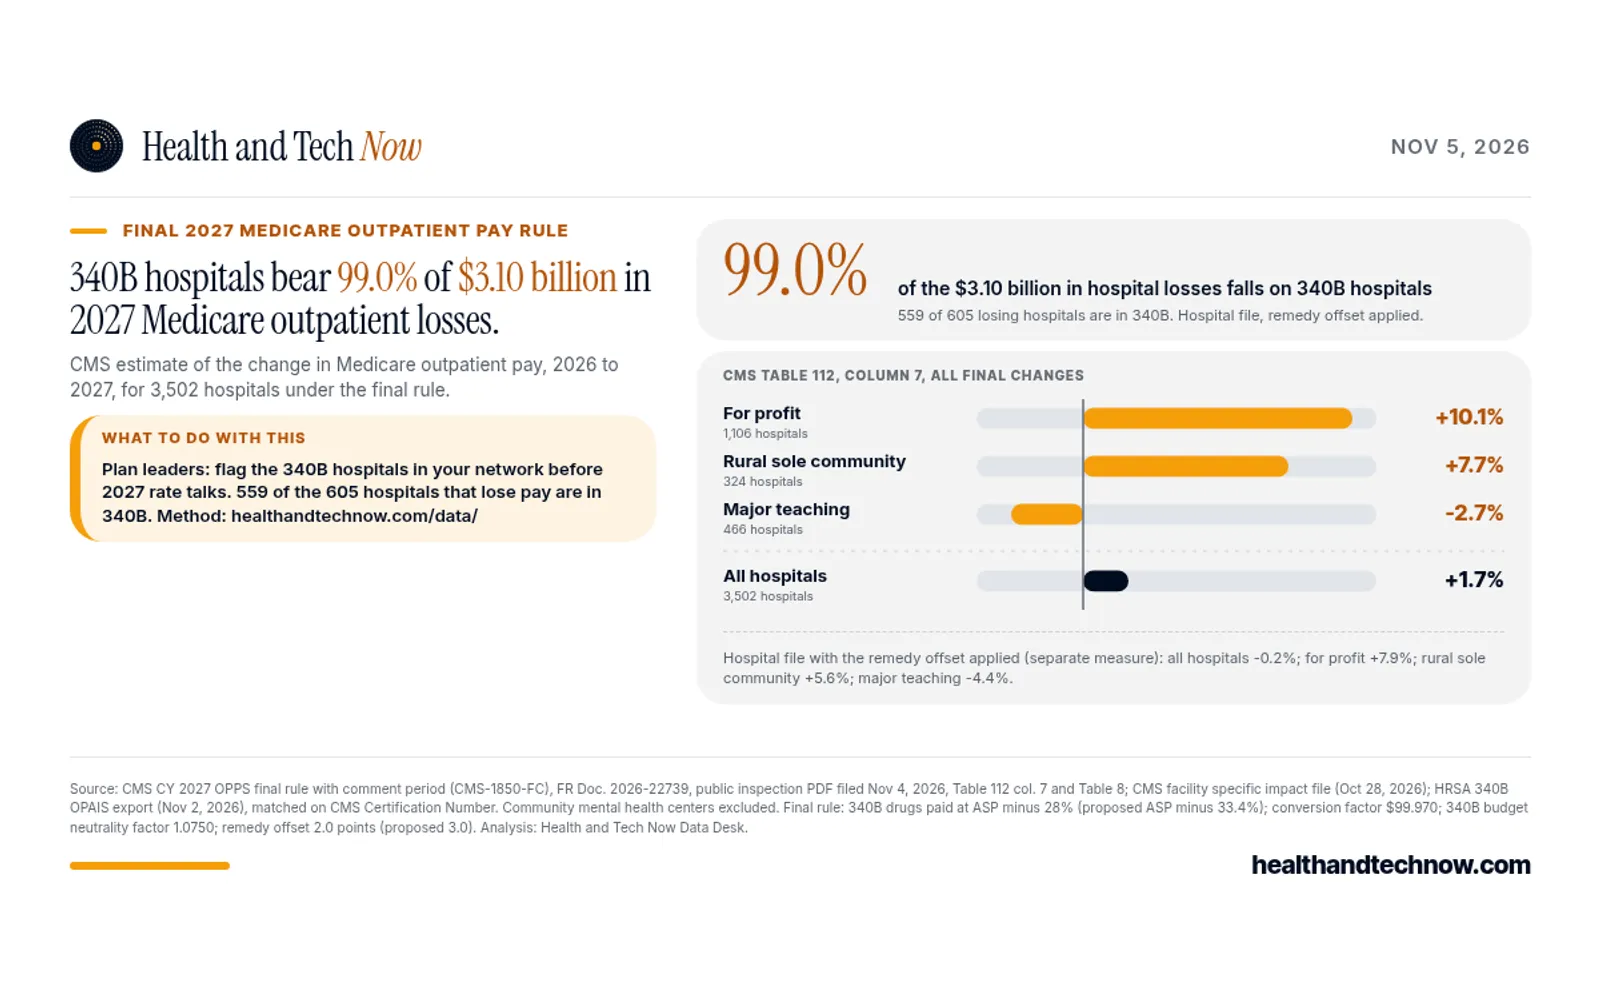
Hospitals in the 340B drug program carry 99.0% of the $3.10 billion that losing hospitals give up under the 2027 Medicare outpatient payment rule. That comes from our run of the hospital level impact file for the final Hospital Outpatient Prospective Payment System (OPPS) rule. The Centers for Medicare & Medicaid Services (CMS) filed the rule for public inspection on Nov 4, 2026.
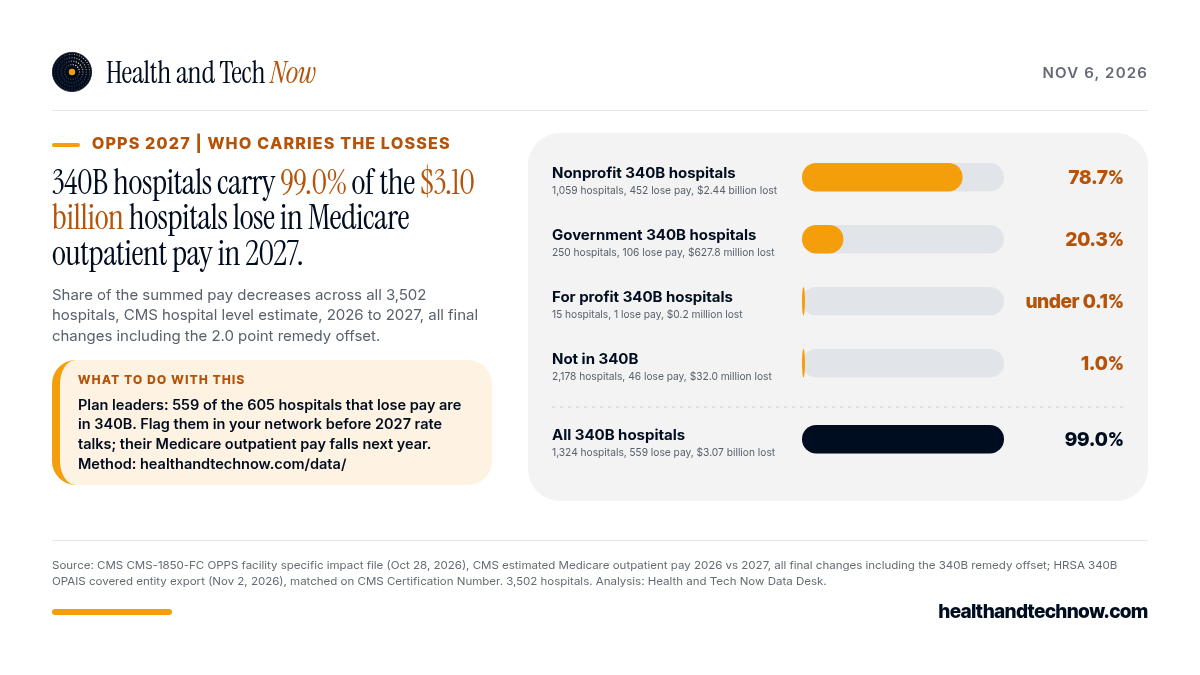
The run counts 1,324 hospitals in 340B. Of those, 559 lose pay. Together they account for $3.07 billion of the $3.10 billion in summed losses across all losing hospitals. The net change for 340B hospitals is a 3.8% drop. Hospitals not in 340B, 2,178 in all, post a net 6.9% gain, and only 46 of them lose.
Why it matters: hospital contracts that pay a percent of Medicare outpatient rates move with these numbers in 2027. The softer final rule did not move the losses off 340B hospitals.
What changed from the proposed rule
The final rule pays for drugs that 340B hospitals buy at average sales price (ASP) minus 28%. The proposed rule set ASP minus 33.4%. CMS also cut the 340B remedy offset to 2.0 points off the update for non drug items and services. The proposed rule set 3.0 points.
Other parameters moved with it. The OPPS conversion factor is $99.970 for the final rule, against $102.004 in the proposal. The 340B drug budget neutrality factor on the conversion factor is 1.0750 final, against 1.0844 proposed. The outpatient department fee schedule increase factor is 2.3%, against 2.4% proposed.
Two ways to read the rule
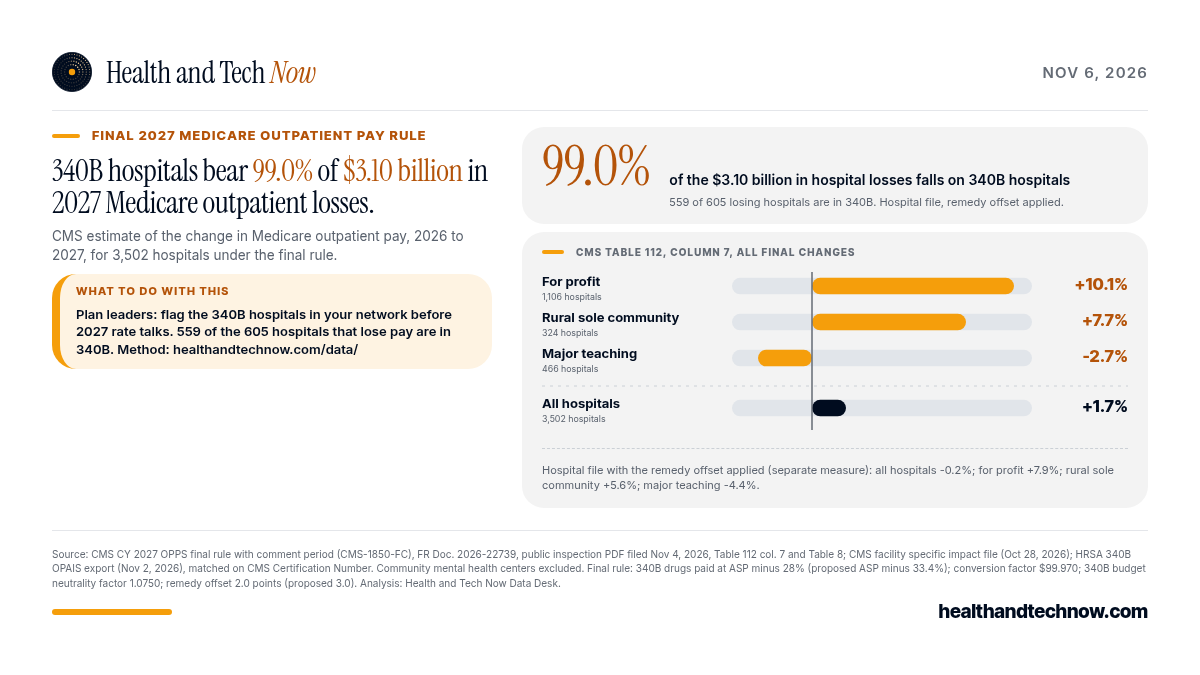
Start with CMS’s own table. Table 112, column 7 shows all final changes. CMS puts all hospitals at 1.7% more, against 1.8% in the proposed rule’s Table 88. For profit hospitals show 10.1% more.
Rural sole community hospitals show 7.7% more. Rural hospitals show 5.3% more. Nonprofit hospitals show 1.4% more. Government hospitals show a 1.7% drop. Major teaching hospitals, 466 in all, show a 2.7% drop.
Column 8 shows a separate 2.0% drop for hospitals subject to the 340B remedy offset.
Now read our hospital file run. We compare each hospital’s estimated 2026 and 2027 Medicare outpatient pay and include the remedy offset. All hospitals land at a 0.2% drop, or $135.7 million less. That is 3,502 hospitals, with 605 losing pay and 2,897 gaining.
The two readings separate because Table 112 column 7 shows all changes and column 8 adds the remedy offset. Our run includes the offset where it applies, so all hospitals land at a 0.2% drop instead of 1.7% more. Every Table 112 row ties to our file run within 0.3 points.
Our run also splits by hospital type. For profit hospitals show 7.9% more. Major teaching hospitals show a 4.4% drop, or $1.31 billion less, with 200 of 466 losing pay. Rural hospitals show 3.4% more. Government hospitals show a 3.4% drop. Nonprofit hospitals show a 0.5% drop.
Who loses the most
Nonprofit 340B hospitals hold 78.7% of all losses. Government 340B hospitals hold 20.3%. The median change for 340B hospitals subject to the drug cut is a 0.7% drop. The median for hospitals not in 340B is 8.0% more.
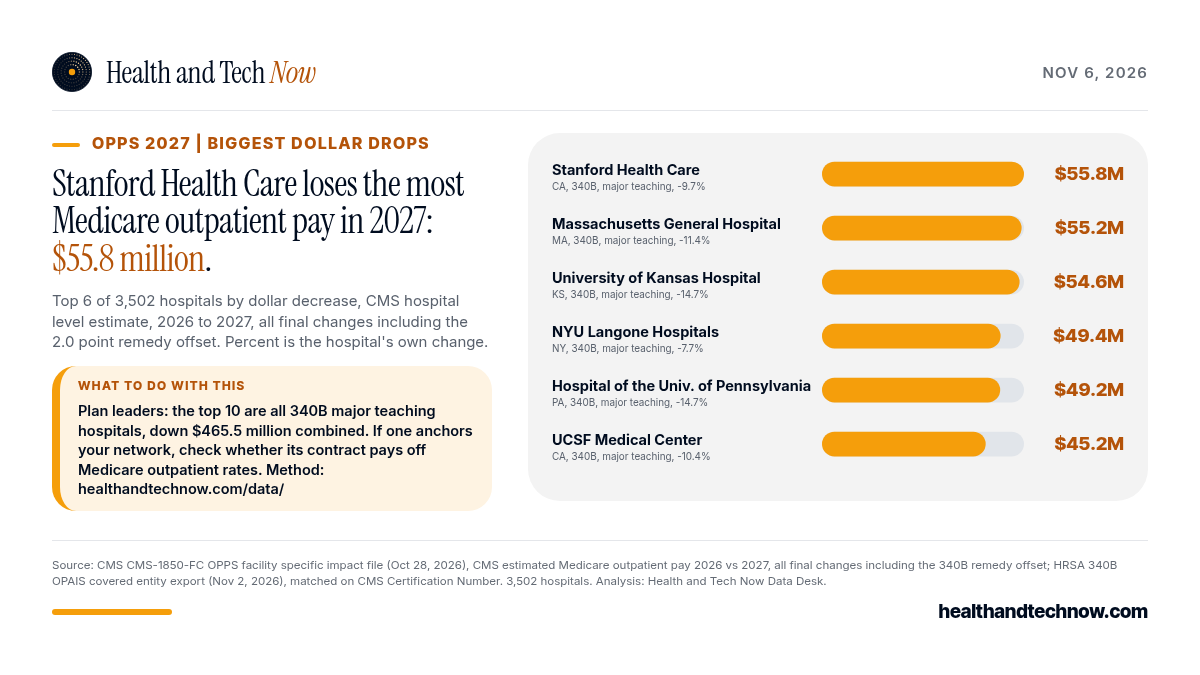
Four hospitals show the largest dollar decreases in the CMS file. Stanford Health Care loses $55.8 million, a 9.7% drop. Massachusetts General Hospital loses $55.2 million, an 11.4% drop. University of Kansas Hospital loses $54.6 million, a 14.7% drop. NYU Langone Hospitals lose $49.4 million, a 7.7% drop.
The top 10 hospitals by dollars are all 340B major teaching hospitals. Together they lose $465.5 million.
The proposed rule, run the same way, put 340B hospitals at 98.8% of $3.45 billion in losses. All hospitals came in at a 1.3% drop and major teaching hospitals at a 6.0% drop.
What plan and vendor teams can do now
- Find the 340B hospitals and major teaching hospitals in the network. The 1,324 340B hospitals carry 99.0% of losses, and the 466 major teaching hospitals show a 2.7% drop in Table 112.
- Check which hospital contracts pay a percent of Medicare outpatient rates. Those contracts move with the 2027 rates.
- Treat the figures as CMS estimates for 2027, not paid claims. Dollars include beneficiary cost sharing.
How we did this
We ran the CMS facility specific impact file for the final rule, “FR27 Impact File 10.28.26”, pulled Nov 5, 2026. We matched facilities to the HRSA 340B OPAIS covered entity export of Nov 2, 2026 by CMS Certification Number. We set 340B status before any split, and name matching changed no status.
The run covers 3,502 hospitals, with community mental health centers excluded. The file does not isolate the remedy offset by hospital, and OPAIS is a Nov 2 snapshot.
Federal Register page numbers come with the Nov 6, 2026 issue. Cites now point to public inspection PDF pages, including Table 112 at pp. 1223 to 1225 and Table 8 at pp. 109 to 110. The rule is CMS-1850-FC, FR Doc. 2026-22739. Hospital names are CMS file names. Full method and every source cell: Health and Tech Now Data Desk.



 GlobeNewswire

