Medicare cuts doctor pay 2.31% in 2027 final rule
CMS set the main 2027 conversion factor at $32.63 as a one year bump expires. ACOs can waive Part B cost sharing from April, and the remote monitoring staffing rule waits until 2029.

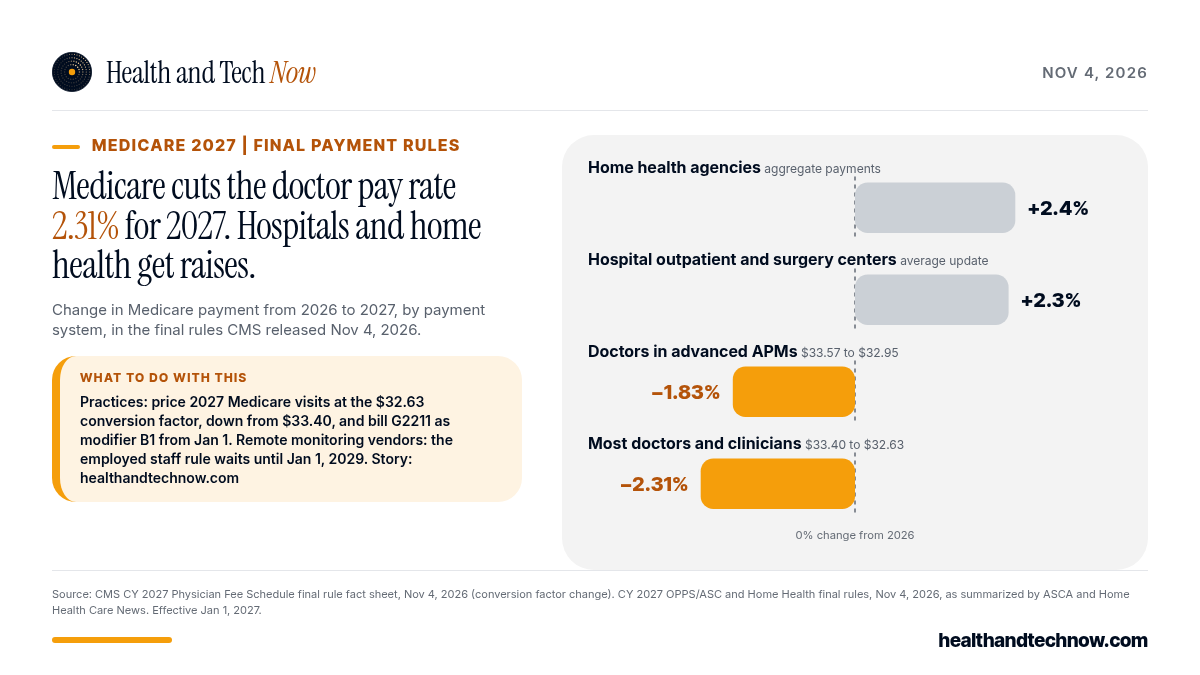
CMS finalized a 2.31% cut to the main Medicare physician fee schedule conversion factor for 2027, to $32.63 from $33.40, according to the CMS fact sheet released Nov. 4. The conversion factor is the dollar multiplier Medicare uses to turn each service’s value into a payment. The rule takes effect Jan. 1, 2027.
The cut follows the expiration of a one-year 2.50% increase for 2026 from Public Law 119-21, which CMS calls the Working Families Tax Cut legislation. CMS said current law therefore requires a 2.50% reduction versus 2026. The agency also applied a 0.25% statutory update for most clinicians and an estimated 0.12% downward adjustment for changes in work values.
Clinicians in qualifying advanced alternative payment models face a smaller cut. The qualifying APM participant conversion factor falls 1.83% to $32.95, down $0.62 from $33.57. That factor includes a 0.75% statutory update.
What changes for patients
Starting April 1, 2027, approved accountable care organizations may reduce or eliminate Part B cost sharing for many items and services for assigned beneficiaries, HHS said in its press release.
Medicare eligibility is limited to four groups under section 71201 of Public Law 119-21, CMS said: citizens or nationals, lawful permanent residents, Cuban and Haitian entrants, and people lawfully residing under a Compact of Free Association.
Shared medical appointments get new codes and payment. Two new advance care planning G-codes, G0572 and G0573, cover clinical staff time.
What changes for practices
When a separately identifiable office or outpatient evaluation and management visit happens the same day as a 0 day global procedure by the same physician or practice, the more expensive service is paid 100% and the other 80%. CMS had proposed 50% and had included 10 day and 90 day global procedures. The agency narrowed it after comments.
The G2211 complexity add-on becomes modifier B1 and raises the evaluation and management base code payment 16%. A new modifier B2 raises that payment 32% for clinicians in Shared Savings Program ACOs or LEAD Model ACOs. B2 is voluntary.
Traditional MIPS reporting sunsets beginning with the 2031 performance period, two years later than proposed, HHS said. Clinicians have through 2030 to move to MIPS Value Pathways, which cover about 98% of clinicians, or to Advanced APMs. CMS added three MVPs: diabetes, hypertension and hospitalists.
The rule also closes an incentive payment loophole. HHS said that prevents an estimated $2.38 billion in unintended windfall payments over the next decade.
Remote monitoring
CMS finalized three remote monitoring items: remote therapeutic monitoring only for established patients, a separately reportable initiating visit at the start of remote physiologic monitoring or remote therapeutic monitoring, and an updated valuation.
A separate policy that would pay for remote monitoring only when clinical staff employed by the practice perform the work, not contractors, is delayed two years to Jan. 1, 2029. We covered the proposal in our earlier story.
Hospitals and home health
The 2027 outpatient prospective payment system and ambulatory surgical center rule carries an effective average update of 2.3% for hospital outpatient departments and ASCs, which is a 3.2% market basket increase minus a 0.9 point productivity cut, according to the Ambulatory Surgery Center Association’s read of the rule. CMS removed 637 procedures from the inpatient only list for 2027, continuing to phase out that list.
Home health agencies get a 2.4% aggregate payment increase versus 2026, about $415 million, Home Health Care News reported of the CMS rule. The figure combines a 2.1% payment update and 0.3% from the fixed dollar loss amount. The rule includes a 3% temporary reduction to the 2027 national standardized payment rate to recoup past overpayments.
Ashley Thompson, a senior vice president at the American Hospital Association, said “CMS’ Medicare outpatient hospital payment rate does not adequately take into account the financial challenges facing hospitals today.” AHA said it was disappointed CMS finalized another expansion of site-neutral payment and continued to phase out the inpatient only list.
The American Academy of Family Physicians said the cuts are driven in part by the expiration of the temporary 2.5% increase for 2026. “This means that physicians will once again begin the year with lower rates as practice costs continue to rise,” AAFP said.
What to do now
Clinicians: check your 2027 Medicare rates and billing codes before Jan. 1. G2211 is billed as modifier B1.
Remote monitoring vendors and practices: contractor staffing stays payable until Jan. 1, 2029. New starts need an initiating visit in 2027.
Medicare members: if your doctor is in an ACO, ask whether it will cut your Part B cost sharing starting April 1, 2027.
 CMS, Calendar Year (CY) 2027 Medicare Physician Fee Schedule final rule fact sheet, Nov. 4, 2026
 HHS, CMS finalizes CY 2027 Medicare Physician Fee Schedule, Nov. 4, 2026
 Federal Register, CY 2027 Physician Fee Schedule final rule (CMS-1848-F), public inspection, publication Nov. 9, 2026
- Ambulatory Surgery Center Association, CMS releases 2027 final payment rule, Nov. 4, 2026
- Home Health Care News, CMS finalizes 2027 home health Medicare payment rule with 2.4% rate increase, Nov. 4, 2026
- American Hospital Association, statement on CY 2027 OPPS final rule, Nov. 4, 2026
- American Academy of Family Physicians, statement on the 2027 Medicare physician fee schedule, Nov. 4, 2026

 KFF

 Minnesota Attorney General
